Showing posts with label sleep. Show all posts

Wednesday, May 18, 2016

A bunch of updates: Miss Sassy Pants, Sleep surprise, GI/Urology, etc.

Ha!  I am going to spare you my usual spiel of "I am so sorry that I neglected the blog and I won't do it again".  However, I will promise you that this post isn't entirely about medical stuff. . . sort of.

The Sleep Study Results:
Why does it take so long to get results?  Three weeks to get the results.  Actually, it was 2 weeks, but the doctor neglected to call me because he was flabbergasted and needed to do a more comparative analysis of her previous sleep study.  Yeah, "flabbergasted" is never something you want to hear from a doctor.


To see her previous sleep study results (as in pre-surgery), click here.  Ellie Bear's hypoventilation (very low rate of breathing) has resolved!  As a result, her inhaled CO2 levels are near normal.  Her oxygen saturations for the majority of the night ranged from 92-94% (compared to 80% in the previous sleep study.  In more exciting news, she now has central sleep apnea.  Girlfriend can never doing anything half-*ssed and likes to keep us all guessing.  So. . . where did the central sleep apnea come from?  We do not know, which is why we are going to do an MRI of her brain just for sh*ts & giggles. . . can you all tell that I am just sick of this stuff.  Why the MRI, you ask?  Central sleep apnea tends to originate from the brainstem (or in some cases the heart).  Essentially, your brainstem forgets to tell your to breath.


Speaking of sleep apnea, I have it and so does Andrew.  A few months ago, Drew woke me up because I "wasn't breathing".  My allergies were horrible and he basically shoved Afrin up my nose and it cured me.  Last month, I was in Vegas with some friends.  Vegas, baby!  The cigarette smoke also mucked up my breathing and my friend informed me that I was obstructing.  Because I don't have enough doctors appointments before school lets out in 2 weeks (I have 5 and Bear has 2), I now have an appt. with my PCP.  I am wondering if this is why the past 3 month I have been averaging about 3.5 hours of sleep?  Very restless sleep.

My Fitness Best Friends (and texting buddies):
Michelle (my Ds blogging buddy and first time meeting her!)
Lindsey (former Canadian, former Austinite)
Lisa (fellow Canadian Beachbody coach!)


Motivation Fitness Takes Vegas:
Oh yes, my friends, I went on a girl's trip to Vegas.  That would be a trip without the child.  As in alone.  I am still a beachbody coach running my health and fitness group called Motivation Fitness.  Our Facebook group is full of amazing ladies.  We not only share our victories and support each other during health-related struggles, we have become friends.  Many of us had never met.  Last month, 10 of us took a 4 day trip to the Sin City.  From Vancouver, Canada, Montana, Florida, New York, Texas, Missouri, and Ohio, all of us had a wonderful time.  While we managed to clock in an average of 24,000 steps a day and while we also were a health group, it was our main mission to eat (and to pee -we are all moms with weak bladders) in every hotel room along the strip.

School: The IEP meeting
Nothing screams "welcome back from vacation" like an IEP meeting the morning after your flight lands.  The IEP meeting went well.  We have good goals in place.  Ellie will spend a majority of her time in a Functional Academic spec ed classroom [FAC], with appropriate push-ins for specials, lunch, and home work and other classes as tolerate.  The "as tolerated" = behavior is good.  On a sad note, Ellie will not be at the same school as next year.  Currently, Ellie goes to a school that is 30 minutes away.  While that is not ideal, her teacher and aides were/are amazing.  Next year, her home school that is just down the street from our house is going to have an FAC room.  Fingers crossed that we have an excellent teacher and aides next year.  Change is difficult.  Being shuffled around from different schools, different classmates, and different teachers can be tough on Ellie.


The Dysfunctional Voiding Clinic: NPs vs MDs and Gastroenterology + Urology
I love joint appointments.  It is so nice to kill 2 specialists with 1 stone.  As a follow up, Ellie is now peeing more.  As in 3-5 times a day now, compared to once every 18-29 hours.  Unfortunately, she likes to do things the opposite of "normal".  When she poops regularly, she doesn't pee.  When she doesn't poop, she pees more.  Go figure.

The Bear has lost weight again.  Not much, but this child should be gaining.  Like a ton.  She is on an appetite stimulant and she eats all the freaking time.  At first I figured "different scale", but after having 4 doctors appointments in 10 days and all 4 scales showing a similar weight, it could no longer be ignored.

Play-Doh Fun!
You can see that she lost a big of weight in her face.  We have also gone down a size in clothes.
This brings me to the awesomeness of Nurse Practitioners.  No, I am totally not biased given that I am also a NP.  I have battled with Ellie GI doc for a few years now.  Always dragging his heels on trying to figure WHY she has severe constipation and WHY she loses weight.

GI NP: She has had a colonoscopy, right?

Me: Nope.  She needs one and will get one next month with her testing

GI NP: She has had stool studies, right?

Me: Nope.

GI NP: How about an upper GI?

Me: Yes!  Just a few months ago after begging the doc for one for 2 years.  We ruled out celiac, h. pylori, and lactose intolerance and discovered esophageal gastritis instead.

So, we did a bunch of stool studies to look for malabsorption.  Good news!  The studies were normal.  Bear's poop is normal.  Yay!


Disney On Ice:  
Two weekends ago, we took Ellie to Disney on Ice.  I wasn't sure how she was going to do during the 2 hours show.  She was so excited!  Before it even started, she was clapping and grinning.  Her enthusiasm was priceless and infectious.  She did great. . . provide Mickey Mouse was on the ice.  When he wasn't, Ellie was telling us "truck, buh bye, Noble Pig".

This all brings me to next month: Surgeries and Hospitalization:

It is always great fun to kick of summer break with a 3 day hospital stay.  Right?!  Okay, this is gross, but we will be admitting Ellie to the hospital for a bowel cleanse.  Think dropping and NG tube from her nose to stomach and pumping her with a full gallon or two of GoLytely.  The following day, Ellie will have a colonscopy and the placement of a colon manometry tube.  Essentially this tube will remain in her colon and be taped to her butt or thigh until the following day when we will hook it up to this manometry machine.  While she is under anesthesia, she will also have her brain MRI with contrast and her yearly routine blood work.  The following day, is the colon manometry which will look at pressures throughout the colon - identifying if there is delayed colon transit and if so, if there is a specific part of the colon where this occurs.  Then, home!

The following week, I get to have surgery.  For the past 2 years, I have been battling woman's health issues.  A variety of treatments have been tried with no relief.  More drastic measures will be taken and I will essentially lose my fertility.  No more kids for us, so if one more person asks if we will have more. . . I feel like I am way too young for this nonsense, but at 35 years-old, I am apparently of
"advanced maternal age" even though I have quite a few older friends who are currently pregnant.

Haircut:
I cut the Bear's hair myself.  We keep it short for a few reasons: 1. She chews her hair; 2. It sticks to her messy Nutella face; 3. Drew loves it short; and 4. It gets scraggly when it is longer.  The reason I am the one to cut her hair is because she hates it.  It is like medieval torture to her.  She does okay with the back, but the sides freak her out.  Perhaps the sound of the scissors? Or maybe having a sharp object near her face?  Sensory issues?  The thing is, if I take her somewhere, she is still a wild banshee child and no amount of fun toys, movies, little riding things help the matter.  I end up paying for the haircut that looks just like my hack job and I feel the need to tip a ridiculous amount because the Bear is a tornado.


Tama Boo:
In sad news, our beloved, black cat, Tama, has been missing for a week now.  She is usually indoors by 9pm and comes when called.  There were storms last Tuesday night and Tama is petrified of thunder.  I have called/ searched for her, all the neighbors in a 1/2 mile radius are looking for her, and I have posted her picture on Next-door.

So even though it sounds like there is a ton of chaos over in the Theurer household, we are staying afloat.  Bear's new favorite word are "oops" and "buh bye".  Any time someone drops something "oose!" [oops].  Any time we leave a room, a toy, or someone leaves a room, it is "buh bye" with great drama and a princess wave.

School is almost over and I am really looking forward to July.  When all this medical stuff is behind us and when I can sleep past 5:45am. . . and instead wake at 6:45am.


 photo IMG_2291_zpsudykfi0h.jpg

Follow us on Facebook! https://www.facebook.com/pages/The-Chronicles-of-Ellie-Bellie-Bear/216738345037166


Tuesday, December 8, 2015

Ellie's Surgery for Sleep Apnea and Recovery

The month of November sped by while at the same time it, seemed to crawl along at a snail's pace.  There were too many things to worry about and I do not mean of the turkey being over-cooked  and a family feud variety.   No, I am talking about Ellie's surgery and my cervical steroid injection procedure.

As someone with a diagnosed anxiety disorder, it wasn't very difficult for the usual worrying and feelings of anxiousness to transcend into full blown panic mode complete with heart palpitations, nausea, sweating, and feeling of impending doom.  Then how the irrational suddenly becomes the rational.

*I apologize in advance for some missing photos - I used Photobucket for free as a means to store my photos and they are now holding a few hundred pics of mine for hostage unless I pay for an expensive plan and I also managed to lose half my photos from my computer*


In the past year, I have had several steroid injections into my back.  Nearly all of them have been in the lumbar (lower) region of my spine as well as my sacroiliac joint.  However, it was the first time I was having a shot into the epidural disc space a my neck in hopes of alleviating the intense neck/should pain with radiating numbness, tingling, and weakness down my entire left arm.  Epidural shots into the cervical region, as opposed to lumbar or thoracic, are a bit more risky given the close proximity of the brain as well as narrowness of the spinal column.  This of course triggered an intense sense of doom.  "It is going to cause a flare up that lasts through Thanksgiving and then I will have to cancel Ellie's surgery.  I am going to have temporary paralysis or a spinal headache!"


Then even more worrisome for me because it involve my baby, Ellie's surgery - the lingual tonsillectomy and glossectomy- which was going to commence exactly one week after my injection.  By the Friday before Monday's procedure, I had talked myself into believing that because I worried, fretted, and had horrid dreams about all the "what ifs"related to all that could go wrong with Bear's surgery and recovery, that I worried all possible complications away.  Of course, then I had myself thinking "well now I just jinxed it and something is going to go horribly wrong!"

As with most things, I worried for nothing.  My shot was awesome with a minimal flare up followed by 50% pain relief and 75% decreased numbness/tingling.  Ellie's procedure went well and she had a relatively smooth recovery.

Pre-operative waiting room Selfies

Ellie's surgery lasted approximately 1.5 hours and she was a little stinker pants coming out of anesthesia.  Then for the next two hours she was agitated and screaming bloody murder.  Kicking, hitting and using her teeth to pull off the sock that was taped around her ankle.  The sock that was covering her pulse oximetry monitor around her toe - the little thing that measures the oxygen saturations in the blood (normal is 98-100%).  Given the thrashing that was already making it difficult of the pulse ox monitor to function proper, I respectfully asked if we could do spot checks every x number of hours rather than continuous monitoring and the doc looked weary.  I totally understand seeing as the child just had her upper airway carved on!  Yet, after spending just 5 minutes in the room with the Tasmanian Devil, the doc said "take it off and check her every 4 hours".


Once Ellie was calmed down using coloring books and watching Sofia the First, she ate some ice cream and drank a bit of juice.  She also started peeing!  As in she peed THREE times that day and 3 times the following day. This is something that we hadn't seen since July (yes, she is still doing that pee every 22-30 hour thing).  When we arrived in pre-op, Ellie hadn't urinated in well over 24 hours.  I knew from past experience that the anesthesia would cause a more acute urinary retention so I convinced the surgical team to perform a urinary cauterization in the OR if she didn't pee while under.  That cath seemed to be a cure . . . for about 3 days.

Busting out!  Poor thing was feeling pretty cruddy, but she was happy
to be headed home after a night in the hospital.

I was extremely concerned about how things were going to go overnight- would she require oxygen since she is so swollen?  Would she be in a lot of pain?  Would she sleep at all?  Again, it was needless worry for our Bearity Bear had oxygen saturations from 91-94% for the entire night!!!  To me, that is proof that her surgery was a success because pre-surgery, she would sit at 81% for most of the night.

Play-doh pajama time with Daddy!  Her cheeks were pretty swollen.


A traditional tonsil and adenoidectomy recovery usually takes 7-10 days with an increase of pain around day 5-10 depending on when the scabs slough off (it was day 6 for Ellie a few years ago).  With the lingual tonsils, there is less raw space and as such, less pain.  The surgeon stated that normal recover for a lingual tonsillectomy is 5-7 days.  Ellie's recovery took about 6 days with her returning to school the following Monday.  I would say that post-op day 3 (Thanksgiving day, of course) was by far the worst where we had a hard time controlling her pain and that left her miserable, crying and rather agitated.  As for the glossectomy, the tongue heals quickly - in a manner of 4-5 days.  It did give her some seriously rank breath that lasted nearly 2 weeks - as in enough to pass out from if she were to breath on you!  She is still snoring a bit, but I believe that is because she has some drainage and congestion due to her throat and tongue healing.  We will have a follow-up sleep study in about 3 months to re-evaluate her sleep apnea.

So that was our November and now I can hardly believe that December is already here and soon 2016!


Follow us on Facebook! https://www.facebook.com/pages/The-Chronicles-of-Ellie-Bellie-Bear/216738345037166
Tuesday, October 20, 2015

The Pumpkin Patch and Updates - GI, Urinary, Sleep Apnea, Cervical issues, Etc


You all should be proud of me as it has only been 3 weeks since my last blog post.  Longtime Ellie Bellie Bear readers, do you all remember back in the day when I wrote at least 3 posts a week?  Progress!  Seriously, everyone, I have 4 or 5 open blog posts sitting in the queue waiting to be completed.  Such as the one that I wrote way back in June on lice.  I really need to finish that one up because Ellie has lice again back in September!


As usual, things have been chaotic, but I made sure that this past Columbus Day we spent part of the day doing something enjoyable.  We had such beautiful weather that Ellie and I spend the day outside and then too a trip to the local nursery to pick out a pumpkin. . . er pumpkins.  Bear was the only child there and there were two lovely ladies picking out flowers and 3 landscaping guys as the Red Barn Nursery.  They all held little secret smiles as she would go running by (and when she ran up to the landscaping dude and gave him high-5s).  My daughter, the entertainment at the local nursery.  The frolicking fairy princess.


Ellie Bear thought it was quite the game to gather up pumpkins of various sizes to add them to our cart.  The Chunky Chicken was under the mistaken impression that was going bring those 5 or 6 of those personal-sized pumpkins and 12 minute pumpkins.  She would dance (yes, dance, frolic, sashay) her way back to the cart with a mini pumpkin in each hand.  Perhaps the most entertaining part of the trip was Ellie's vast fixation on gourds.  Especially the funky looking green one.  She was adamant that we take that one home with us.  As well as the one that I think looked kind of like a light tan-colored, bowing goose.


Now, what is the Bear going to be for Halloween?  That is a great question because I don't know the answer to that either!  Ellie hasn't been into dress up lately.  I was thinking Flash dance given her propensity to don leg warmers during dance class.  However, I imagine she will saunter about the neighborhood in her glow-in-the-dark Mickey Mouse pajamas like the little diva that she is.

Ellie spends time in both special education classroom [FAC] and general kindergarten.  Of course I signed up to be room mom in the kinder class.  Several people have asked "are you kidding me?!  Don't you know that room mom is a lot of work?".  Yes, it is yet it is always a great way to meet people and be involved at the school. (Maybe now isn't the time to also mention that I am the inclusion parent liaison as well).  Ellie's school no longer offers Halloween parties.  Pumpkin Math does not count, folks.  So this past Saturday, all of us room mom's in Ellie's kinder class though it was be fun to host a mini Fall -Festival at a local park with snacks, crafts, and goodie bags and with costumes being optional.  All of the children had great fun and it was exciting to hear several of the boys say "Ellie's here!  Hi Ellie".  Ellie liked her alone time, but she still did well socializing with the other kiddos.  Several parents all came up to me to share that their child talks about Ellie at home saying that "she is in the class some of the time, but she is in two classes. I like it better when she is in my class". Andrew and I had the chance to meet many of the parents. To say that her school and her kinder class is welcoming is an understatement.  We are thrilled to be a part of this community!


Pumpkin Dancer


Now for some very quick updates.  I promise to write more in-depth posts later, but since I have been asked by a few people for news, here you go:


GI / Urology
For a while the constipation was worse.  We were doing a lot of enemas just to get her to go.  When I called GI, they recommended lactulose.  I imagine you all heard my maniacal laughter at you own homes as this child has been on lactulose in the past (you know that neon green liquid that she has to swallow 1 TABLESPOON twice a day) and it did not work.  The telephone call seemed to be the best treatment because she has been uncorked now.

Urology - she was seen 2 days after my post! No real answers.  Kidneys are good.  Yay!  Possibly related to constipation (um, not completely because she has been backed up way worse and was still urinating several times a day) and possibly a disconnect between bladder contraction and urinary sphincter.  We watch and wait.  If she gets kidney damage, we will look into doing routine, daily catheterizing - please say a prayer that we do not get to that!

Weight - so she has either gained a 1/2 pound or 1.5 lbs. depending on the scale since we started the appetite stimulant in July.  Wooohooooo!!!!!!  AND she has grown in height as all her pants are too short.  First time in over 2 years that I have needed to purchase new clothing for Ellie


Sleep Apnea/ENT:
Last week we met for the Sleep Apnea Clinic which is a double appointment with an airway ENT and the sleep pulmonologist.   It didn't go as planned as the ENT got called away to an emergency.  These things happen, but I was practically in tears after we left the clinic.  We waited months for the appointment.  Her apnea/snoring is worse.  And I pulled her out of school for nothing.

Later that night I got a call from the nurse.  The ENT reviewed the Cine MRI of her head and neck.  She has complete obstruction at the level of the epiglottis.  It could be epiglottis insufficiency from laryngomalacia (aka floppy airway) or due to large lingual tonsils (tonsils below the base of the tongue - not the ones you see when you open your mouth) pushing on the glottis.  We will do a laryngoscope at the rescheduled visit which is in 1.5 weeks.

Surprise MRI Finding: upon looking at the Cine MRI, it was determined that she has widening at the C1-C2 vertebrae suggesting instability.  Aka Atlanta-Axial Instability.  About 15% of people with Down syndrome have this, but for only 1-2% of the people, this is an issue. Right now, Ellie is scheduled to get repeat lateral neck X-rays to determine if she does indeed have AAI.  It does make me wonder, can the instability cause Ellie's bowel and bladder issues?


Me: I think this also needs to be its own blog post, but it will explain why I have neglected the blog lately.  I am still having massive issues with my lower back and sacroiliac.  The sciatica is mostly resolved.  I did receive a nerve block back in May, but it wore off after only 2 months.  The last 4-5 months my neck has been a mess. With lots of pain and signs of arthritis from C3-T1.  Certain movements cause pain and/or numbness down my left arm.  I have had several shots, chiropractic appointments, therapeutic massages, and visits with my pain and physical rehab doctor.  I have also been diagnosed with fibromyalgia.  I was in a car accident last month which exacerbated everything.  Last week I got a neck X-ray which showed that my clavicle is really messed up where it connects to the breastbone and I am waiting for MRI results of my neck and lower back.  Some days are difficult to get out of bed, but I am trying my best to eat well and continue with my PiYo exercises.


Follow us on Facebook! https://www.facebook.com/pages/The-Chronicles-of-Ellie-Bellie-Bear/216738345037166

Wednesday, September 9, 2015

Results of Ellie's MRIs, Ultrasound, and Blood Work


Last Friday, Ellie had a battery of test run at the Children's Hospital - to learn more, click here.

MRI of the lumbar spine = normal (Yay, no tethered cord!)

Renal / Bladder Ultrasound = normal (Yay, no kidney problems!)

Cine MRI for sleep apnea = awaiting results

Routine blood work of CBC, metabolic panel [this also shows kidney function], Thyroid panel, and vitamin D = normal

Weight Gain since starting predication = possibly 3oz give or take a few

Explanation for why this child is only peeing once every 19-24 hours = unknown

Explanation for Ellie's crazy GI issues = unknown

Do you see that the Princess Bear lost her first tooth?!


Ellie's pediatrician has recommended that she be evaluated by a urologist. I have been in touch with the only pediatric urology clinic in Austin and the first available appointment is in November. I think the scheduler was a bit flabbergasted when I explained what the appointment was for because she then had a nurse talk to me. I am pretty sure it was when I said "Ellie has decreased voiding frequency to one every 19-24 hours at a rate of 0.7 cc/kg/hour" that did it. . . The nurse then said "she really seems to have a lot of things going on so I will talk to the urologist and see if we can fit her in earlier".  I am waiting for a call back. What do you want to bet that some of this is related to her constipation and Periactin? Or maybe she is just being a urine withholding toot?

I also put a call into the sleep clinic and am waiting to hear back as we are trying to move up her follow up appointment (it is in December). The MRI results will be discussed at this appointment.

Debating on taking a vote on what Ellie's GI specialist will do given her lack of weight gain and GI issues. All in all, I am relieved that there is nothing wrong with my precious baby girl, but frustrated because we still don't have answers. Lack of answers means we don't know how to help my Bear.


So now. . . . we wait. . . 


 photo IMG_2291_zpsudykfi0h.jpg

Follow us on Facebook! https://www.facebook.com/pages/The-Chronicles-of-Ellie-Bellie-Bear/216738345037166

Thursday, August 27, 2015

An Overall Update - failure to thrive, kidneys, GI issues, sleep apnea

I cannot believe that it has been over a month since I last updated the blog.  Things have been chaotic over here so I am going to just pump out a big fat update.  Normally, I like to add in a lot of cute pics, medical photos, and lots of resources, but I will skip that for now.  Forgive me?

Obstructive Sleep Apnea:
Operation CPAP has been a massive fail.  Am I shocked?  Nope!  We had a sleep clinic appointment back in July to discuss options.  I consulted with a sleep tech who works specifically with getting children to wear their  CPAP face masks.  We made sure that the mask was adjusted properly, but I pretty much had to restrain Ellie the entire time.  The doc witnessed the huge fit that Ellie pitched when I attempted to bribe her to wear place the mask over her nose.  I considered it a HUGE success that she actually wore it for an entire minute in clinic.  The thing is, Ellie wore it more when we first started this CPAP desensitization and she has become progressively more frisky and clever at yanking it off.  Did I mention that this is just the mask?  As in the mask isn't hooked up to the machine and the machine turned on?  Oh I didn't mention that?  In speech therapy a month ago, we were able to get her fully hooked up with the machine on for 10 seconds - with us holding her hands down and her crying.


At this point, we are waiting for her to undergo something called a Cine MRI while under sedation.  This MRI will look at the anatomy of her upper airway and how it works while she is sleeping.  We will use these images to identify what structures are causing the most obstruction.  From there, we will determine what type of surgery will best alleviate her sleep apnea.  Sounds like fun!

My "baby" started Kindergarten!

Weight and Failure to Thrive:
When we last left off, we were starting Ellie on an appetite stimulant.  Can I just say that on day 5, things started to happen.  I have never ever seen a child each so much!  Ellie's starts eating dinner at 4:30pm and will continue to eat until 7pm.  She is back to eating breakfast, now lunch, and occasionally a snack. Her current breakfast is what she used to consume in an entire day.  I do not know where she is putting it all.  Like a bottomless pit.  Human garbage disposal.

Because of her hunger, we are now able to get her to try new foods.  She has always been a picky eater and that includes freaking out over different foods intermingling with each other - like having icing on top of her cake.  Or pretty much having something other than Nutella touching bread products.  So I about passed out from shock when she stole my healthy spaghetti bolognese, and just chowed down, I was shocked.  Different foods of different textures all touching!


This past Monday we went in for her well child check. Even though she has been eating like a teenage boy going through a growth spurt of the past 6 weeks, she has not gained any weight.  Not even an ounce and her height has stayed the same.  I was shocked.  She is eating so much and I thought that her face looked much fuller.  So she still has not gained back all the weight she lost back 15 months ago, BUT she isn't losing any weight so that is something.  I am still placing the blame at whatever is going on with her GI tract.


GI Issues:
When will it ever end!?  The basic update is: we still can't get a handle on it.  She is still requiring lots of intervention which also include enemas.  I am frustrated.  Andrew is frustrated.  The pediatrician is frustrated.  In fact, her pediatrician is so frustrated that she called Ellie's gastroenterologist herself.  At every visit, for the past 15 months, her GI doc has said "if she doesn't gain weight, then we will do an upper GI to officially rule out celiac".  We have had 4 visits since then and quite a few phone calls - each time Ellie has not gained weight and each time he has delayed the upper GI.  After speaking with the pedi on Monday, he has decided to rule out tethered cord (abnormal attachment of the distal portion of the spinal cord to surrounding tissues ordering) by ordering a MRI of the spine.  Unfortunately, due to scheduling issues at the imaging center, they are not able to do the spinal MRI the same day as her Cine MRI.  I seriously doubt she has a tethered cord as she does not exhibit any other symptoms such as dimples or hair patches on her lower back, weakness of her legs, or obvious changes in her gate, but it is important to rule these things out.  She does have signs of urinary retention (more on that later) and of course the GI issues.

Now this all brings me to my next topic:

Decreased Urination:
Ellie hasn't been what one would call a "frequent" urinator in the past couple years.  She has been able hold her urine for 4- 6 hours for ~ 2 years. Then the time between voids grew farther apart.  Last year, for instance, she would pee 2-3 x during the day and then over night.  When she did urinate, it was huge.  She as having to wear nighttime pull-ups during the day because of her adult-sized bladder.  The past 3 weeks, however, things have changed.  She has been waking up dry.  I thought this was a huge potty training milestone.  Basically, she is now peeing once very 18-24 hours.  She may pee at 4pm and then not pee again until 12 noon the following day.  When she does pee, it is a fair amount.  As in it fills up a diaper.  She will be 6 years-old in a few weeks.  She drinks plenty of fluid for a 30 lb kiddo.  She should be peeing much more.  More in terms of both frequency and in volume.

She is signing "school" and "dance".  Someone was excited for her first day!


I brought this issue up with Ellie's pediatrician.  Ellie isn't potty trained so I do not believe this is an issues of 1. her going and not telling us or 2. holding her urine on purpose.  It is most likely some urinary retention caused by either one of her medications or by constipation rather than a kidney issues.  However, it is important to assess her renal function.  So in addition to Ellie's annual CBC and thyroid panel, we are adding in lab work that will look at her kidney function - think BUN and Creatinine.  A renal and bladder ultrasound has also been ordered.  I know from a previous abdominal ultrasound back when Ellie had her weird clay-colored stools that her kidneys are small for her age (but not necessarily small for someone her size).  The good news is that this ultrasound can be performed the same day as her Cine MRI.

So how's that for an update?  I hope to report back more late next week with regards to the cine MRI and ultrasound.  Until then, fingers crossed that we get her spine MRI on the schedule soon!


More on Ellie's GI Issues:
Sitzmarker Study and Delayed Colonic Transit.
Stomach Issues, Surgery, Anorectal Manometry

More on Ellie's Sleep Issues:
Sleepless in Austin
Polysomnography, Sleep Study Results, Obstructive Sleep Apnea and other things
CPAP for Obstructive Sleep Apnea
Photobucket Follow us on Facebook!
https://www.facebook.com/pages/The-Chronicles-of-Ellie-Bellie-Bear/216738345037166

Monday, April 20, 2015

CPAP for Obstructive Sleep Apnea

*I apologize in advance for some missing photos - I used Photobucket for free as a means to store my photos and they are now holding a few hundred pics of mine for hostage unless I pay for an expensive plan and I also managed to lose half my photos from my computer*

Has it really been over a month since I last blogged about Ellie's sleep issues???  Apparently, it has.  This is where we left off: Treatment plan and health risks associated with obstructive sleep apnea [OSA].  To learn more about Ellie's sleep issues, read here.  But first, a few little photos from Easter:


We finally got in to see Ellie's ENT doc at the beginning of March.  Her sleep specialist fought to get her an appointment back in mid-February, but the ENT was out of town.  Anyway, the purpose of the ENT appointment was to evaluate whether or not Ellie's adenoid had grown back.  If so, we would then proceed with a repeat adenoidectomy (because surgery is so much fun!) in hopes that would "cure" her OSA and "oxygenation instability".  I had 2 choices: lateral neck x-ray or a flexible nasal laryngoscopy.  I went with the laryngoscopy.  Yes, it sounds mean, but it is quick.  It provides more detail information.  Plus no radiation is involved. Plus, I have this perverse obsession with seeing people's insides (it is the nurse practitioner in me - especially being a former ENT NP).

Ellie's procedure was the pic on the right.

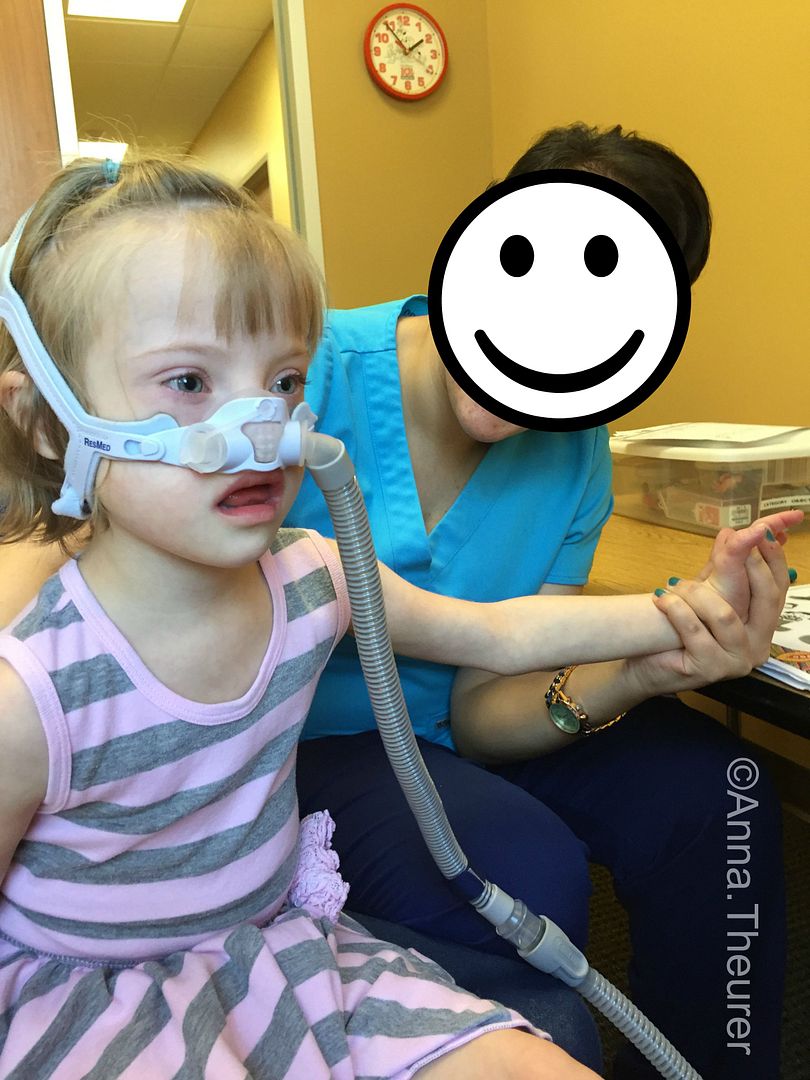
This is how it went: the nurse kindly sat with Ellie.  Her legs over Ellie's and her arms around Ellie's. I then stood behind the nurse with my hands holding Ellie's head straight. Now, a laryngoscope is essentially a spaghetti-like noodle with a camera on the end.  It passes through the nose and looks at the structures of the upper airway.  It can be used to diagnosis enlarged adenoid and tonsils, enlarged base of tongue, laryngomalcia (floppy airway), abnormalities of the vocal cords, and even reflux.  How did Ellie Bear do, you ask?  Well, she fought it all while screaming "NO THANK YOU!  NO THANK YOU!  NO THANK YOU!"  Girlfriend is nothing, but polite.

The findings were not what I was hoping for.  It may sound strange, but I wanted that adenoid to be there.  She is obstructing.  She has had nearly nonstop sinus infections again since August.  If it had regrown, we could have "easily fixed" it.  Nope.  The adenoid did not grow back.  While she does not have an abnormally large tongue, she does have a large tongue base.  She also has not only a high arched palate, but a long palate that dips into the upper airway.  At rest, between the tongue base and the palate, she is already in a partial obstruction - this is while awake and upright.  With sleep, the muscles relax and while laying down, it allows everything to collapse back into her airway.  We also learned that she had reddening of the epiglottis suggesting reflux.  Goody.

Depicts large tongue base causing obstruction of air flow
Photo courtesy: Dental Magazine - unable to find vol #

Take the above pictures and add it to the pic below and that is Ellie's anatomy

Depicts soft palate obstructing air flow

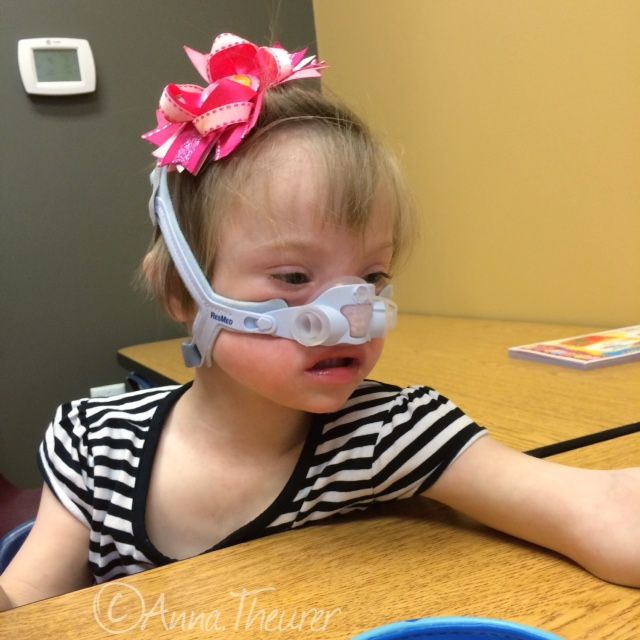
So guess what we have been doing these past few weeks?  CPAP mask desensitization!  The fun never stops.  By the time all was said and done - the doc writing the script, insurance approval, equipment ordered, and equipment training, we finally started on March 26th to desensitize Ellie towards wearing her CPAP mask.  Let us pause for a moment to think about how that.  Desensitize.  Ellie.  Is it going to take years like bath desensitizing did? Save me now!

It's Fighter Pilot Mickey


Continuous Positive Airway Pressure [CPAP] is considered to be a type of ventilation therapy in which positive pressure is blown into the airway as a treatment for obstructive sleep apnea.  We are trying what is called a "Pixi" mask.  This is a mask that fits over her nose only, as opposed to a mask that fits over both the nose and mouth.  You need to create a tight seal or otherwise the pressurized air will leak around the mask.  If she starts to mouth breath, the air will escape so there is a strong possibility she will need the full face mask. 

During Speech and OT.
We have adjusted it since then so that it isn't digging into her face.

You can just imagine how this is going.  My daughter has some significant sensory avoidance issues when it comes to her face, hair, and head.  Tooth brushing requires some interesting gyrations, which involve my legs over hers and my arm holding down her arms.  Combing or washing her hair is considered a form of torture.  Now she has to wear a mask over her face?  One that blows pressurized air into her face?  Right. . . 

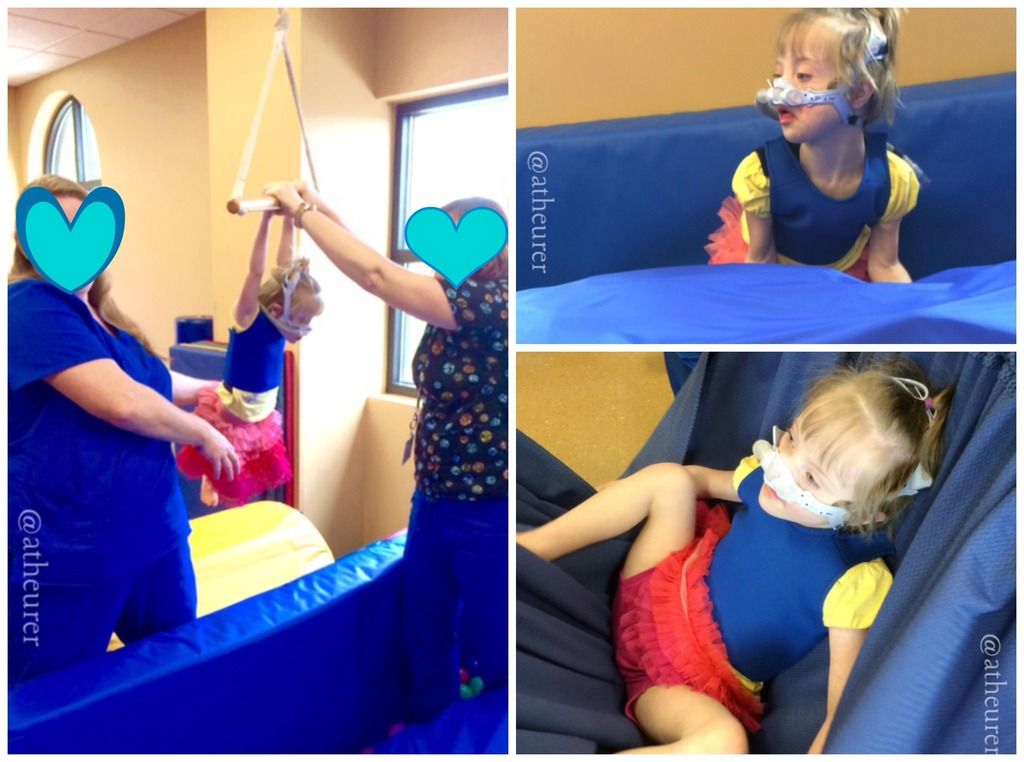
Co-therapy between speech therapist and occupational therapist
in the sensory gym.  Also trying out a compression vest since Bear has
been behaving like the Tasmanian Devil on steroids.

So desensitizing is a  s l o w  process.  A step by step approach.  Ellie is to build up to wearing her mask for 15-20 minutes, 3 x day.  Then we add hooking it to the machine and turning it on - again 15-20 minutes, 3 x day.  After that, falling asleep with the mask hooked up to the machine and turned on.  We are making progresses. . . sort of.

"yeah, I'll totally wear it if Papa is next to me."

At therapy (ST/OT), she will wear the mask without too much difficulty.  She has worn it for 2 therapy sessions for ~30 minutes!  At home, she will touch it, but shout "NOOOOO!" when she sees me hold it.  She will allow Mickey Mouse to wear it. She will try to put it on Minnie Mouse.  Once, she tried to put it on herself - in the waiting room at therapy.  Apparently, she associates therapy with the CPAP mask now.  Once, she allowed me to put the mask over her face just before we went for a ride in the car.  I am also able to place the mask on her once she is already asleep, but am not able to turn on the actual CPAP.  Progress is progress.  No matter how slow it is.  

Traitor!  You said this would be fun. You said I was going to be a fighter pilot.
Our sleep doctor told us to follow up in 2 months time.  It is said that if she will not wear the mask with CPAP within 2 months, she will most likely never wear the mask (well at least in the near future wear the mask.  Maybe in 10 years she'll wear it, but that doesn't really help the now).  That means Ellie would have something called a Cine MRI, which is basically an MRI in motion to look at the airway while the patient is under deep sedation.  The Cine MRI helps determine if surgery is necessary and if so, what part of the upper airway needs to addressed.  So yeah, I want the CPAP to be tolerated and to work.


My little dancer who recently discovered her shadow.


Photobucket

 Follow us on Facebook! http://www.facebook.com/annatheurerfitness http://www.beachbodycoach.com/annatheurer https://www.facebook.com/pages/The-Chronicles-of-Ellie-Bellie-Bear/216738345037166

Tuesday, February 24, 2015

Part 2: Treatment Plan and the Health Risks Associated with Obstructive Sleep Apnea


The sleep study results landed Ellie with the official diagnosis of Obstructive Sleep Apnea with hypoventilation and oxygenation instability.  Isn't that a mouthful? 


Obstructive sleep apnea [OSA] and sleep disordered breathing [SDB] can have a huge impact on health.  Actually, it can be very detrimental to one’s well-being.  I still shutter when I think about what Ellie is at risk for if we do not treat her OSA.


The symptoms above are what we in the health care field refer to as "red flags".  Some of the symptoms may mean nothing at all or may signal a sleep disorder.   Yes, snoring is a sign of OSA, but not everyone who snores has OSA and not everyone who has OSA snores.  That being said, chocking and gasping while sleeping is a neon sign indicative of OSA.

In addition to the signs listed above, kids can present with a few other symptoms (Ellie's are in purple): 
  • anger control issues
  • difficulty swallowing 
  • irritability
  • daytime sleepiness
  • frequent runny nose
  • mental brain fog
  • hyperactivity
  • impulsivity
  • inattentiveness
  • poor school performance
  • memory loss
  • headaches
  • learning difficulties
This pic is from 2 years ago before her T & A.  Notice that she is propping herself up or sitting up to sleep?
These are also signs of sleep apnea in children.

If you have been following this blog for any amount of time, you know that my daughter has severe ADHD  and had shown signs prior to turning 3 years-old.  You also know that when she has poor sleep, it is like ADHD on steroids—as in it is like she never took her Adderall.  Her ability to function at school is pretty much nonexistent.  She has trouble participating in class.  Trouble sitting in circle time, lunch, art, music, therapy.   Trouble concentrating and following directions.  Impaired social interaction as she is “grabby, impulsive, irritable”.  

In fact, studies (several posted in the medical journal Pediatrics between 2009-2013) suggest that there is a blurring of lines between ADHD and OSA. According to the American Sleep Apnea Association, at least 25% of children misdiagnosed with ADHD actually have a sleep disorder, specifically obstructive sleep apnea.  This may be because poor sleep may damage neurons within the prefrontal cortex of the brain.  I have no doubt that Ellie’s sleep apnea and early wakings manifest as ADHD behaviors.  All of that being said, I do believe that she has underlying ADHD just because of our family history.  It makes me wonder though, if we treat her OSA and we treat her ADHD, how well will she do in school?  How will her friendships evolve?  How will our home life change and be improved?

Photo: ADHD Caregiver Day


This goes beyond behavior though.  Obstructive Sleep Apnea MUST be treated.  It CANNOT be ignored.

Untreated OSA and the resulting high levels of inhaled CO2 and poor oxygenation can lead to:

  • Increased heart rate and blood pressure
  • Cardiovascular disease
  • Increased risk for stroke
  • Increased blood pressure
  • Unstable blood glucose and insulin levels, leading to diabetes
  • Memory loss
  • Kidney problems
  • Hormonal imbalance, especially with testosterone


All health issues that can eventually lead to poor quality of life as well as death.  Death! Oh goody.  Bear is only 5 years-old, so what will her life be like at 20, 40, 50 if this isn't managed?!

In children, the usual culprits are enlarged tonsils and adenoid obstructing the upper airway.  Nearly 2 years ago, this April, Ellie had a tonsillectomy and adenoidectomy [T&A].  She had a never ending sinus infection that was resistant to antibiotics and nasal sprays and it lasted months.  She also had frequent ear infections that have required a set of ear tubes every 6-9 months.  In those last 2 months leading up to her surgery, she was propping herself up to sleep.  The T and A  essentially cured her.  After surgery, she didn’t have a sinus infection for 11 months.  ELEVEN months!  Ellie’s last set of ear tubes was in April 2013. 


Sadly, all of that has changed.  This past August is when she started up again with the recurrent, frequent sinus infections.  August is also when her sleep issues started.  She had fluid in her ears this past fall and an ear infection around Christmas.  In December, I asked her ENT doc if her adenoid might have grown back. . . I was told it is rare and too soon.  We were advised to wait until the summer and if she was still having sinus issues, we would reassess. 

Oh yes, I did say it. THE ADENOID CAN GROW BACK!  Yes, it isn’t common, but I laugh in the face of low percentages and low risk.  After all, my odds ratio of having a child with Down syndrome was 1/1300.  A 2011 study in Laryngoscope, show the rate of adenoid regrowth requiring a secondary adenoidectomy to be 1.3%.  Another study in the International Journal of Otolaryngology revealed that those with adenoid regrowth tended to be younger at the age of their initial adenoidectomy as well as had a much larger adenoid than the general population.  Ellie was 3.5 years-old at the time of her T&A and I was informed that her adenoid was “very massive with extreme crusting” aka large and nasty. 


Ellie’s Treatment Plan :

  1. Follow up with ENT to rule out adenoid regrowth and palate abnormalities.
  2. If there is no adenoid regrowth, begin desensitization for CPAP (more on that later.)
  3. If CPAP is not tolerated, discuss further surgical options dependent upon cause of obstruction a. Palate Surgery for long palate obstruction  or  b. Genioglossus advancement aka base of tongue advancement surgery.  Again, more on this later


Ellie’s Sleep Doc wanted her seen by ENT the week we got her results (2/9) or last week.  Unfortunately, her ENT is out of town for the rest of this month.  Thankfully, ENT and sleep doc coordinated and made sure the Ellie is seen the first day Dr. Z is back in office.  So on March 3rd, Ellie will have her ENT visit.  Meanwhile, we have that many more days until we get answers and even longer before we can treat her OSA.


Bring on the coffee!


Part 1: Polysomnography, sleep study results, and obstructive sleep apnea

Tonsil and Adenoid Removal (T&A) Recovery Tips

From a few years ago--I want to go back to sleeping!


Follow us on Facebook!
http://www.facebook.com/annatheurerfitness
https://www.facebook.com/pages/The-Chronicles-of-Ellie-Bellie-Bear/216738345037166

Tuesday, February 17, 2015

Polysomnography, Sleep Study Results, Obstructive Sleep Apnea, and other things

Sleep Study Results Revealed and Explained

We have known about Ellie’s sleep study results for about a week now.  There has been a lot of information to process and of course, a lot of researching on my end.  (Hey, I used to order sleep studies, not interpret them!)

Oh where to begin.  For a recap of her sleep issues, visit here.  For more information about the sleep clinic appointment, visit here.

My little sleep deprived movie star.


According to the doctor:

“Ellie is a 5 year-old with trisomy 21.  She has evidence of mild pediatric obstructive sleep apnea.  However, the patient has evidence of nocturnal hypoventilation and moderate-to-severe oxygenation instability as a result of her sleep disordered breathing.  She requires intervention for her OSA.”

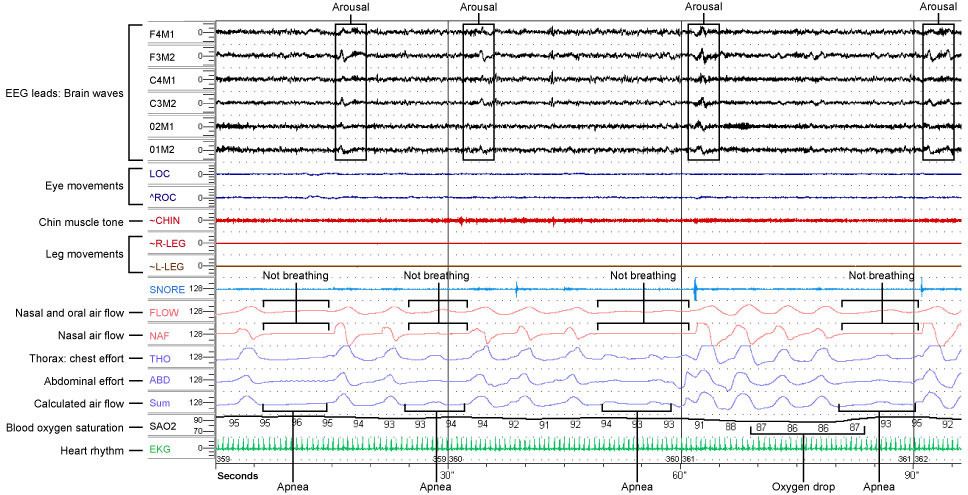
Polysomnography showing apnea with oxygen desaturations and arousals following apnea.
Photo: www.northcountryneurology.com

Translation:

Ellie sometimes stops breathing while she sleeps aka has apnea. According to her sleep study report, she only had 3 apnea episodes, each lasting approximately 10 or more seconds.  It is obstructive because her physical anatomy (small mid-face, tongue, palate, etc) affects her ability to breath while laying down.  Central apnea would involve a problem with the brain signaling the chest muscles to move and this type of apnea has been ruled out.  Pediatric apnea is defined as a pause in breathing.  In children, the pause can be any length of time while in adults, apnea is defined as pauses in breathing that lasts ≥ 10 seconds.  

Hypoventilation is the reduction of airflow by 50% for two respiratory cycles accompanied by reduction of saturation by 3% or arousal from sleep.  Right. So in layman’s terms, the amount of air that flows into the lungs is 1/2 of what it should be and as such, her oxygen saturations [SpO2] go down. 

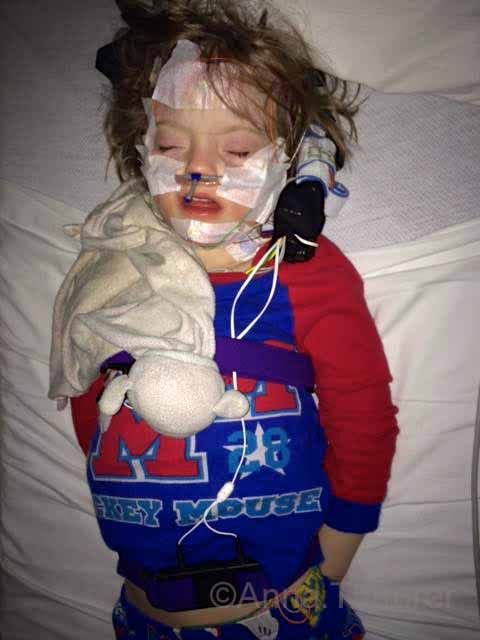
Ellie's overnight sleep study.  How can one sleep with all those wires?

Respirations, Carbon Dioxide, Oxygen Saturations: 

Ellie is diagnoses with nocturnal hypoventilation because she takes very few breaths while asleep and those breathes are very shallow aka she has hypopnea.  Each hypopneic episode lasted 20 + seconds. This causes poor inhalation and exhalation as well and a decrease in oxygen saturation.  

Oxygen Saturations:  looking at oxygenation levels during hypoventilation. Say that Ellie’s normal O2 sats are 100% (okay, her sats really do sit at 100%), if she drops to 97%, it is logged as hypoventilation ( or say when she dropped into the 80’s as seen during her sleep study). 

Carbon Dioxide Levels:  Breathing also involves the exchange of oxygen and carbon dioxide [CO2].  As you breath O2 into the lungs, you expel carbon dioxide out through your nose and mouth,  My daughter’s inhaled CO2 levels are very high.  For 81% of the time she is asleep, her CO2 levels are 50-62mmHG.  Normal CO2 is 35-45 mmHg.  Think of it as breathing face down into a pillow . . . for a huge chunk of the night.  

Respirations:  A normal respiratory rate for a 5 year-old is ~ 20 breaths per minute.  While asleep, Ellie’s was at 9-12 breaths per minute.  Too few breathes = hypoventilation = increase CO2 + decreased O2

Photo: www.proacthealthsolutions.com

Quantity vs. Quality and Arousal.

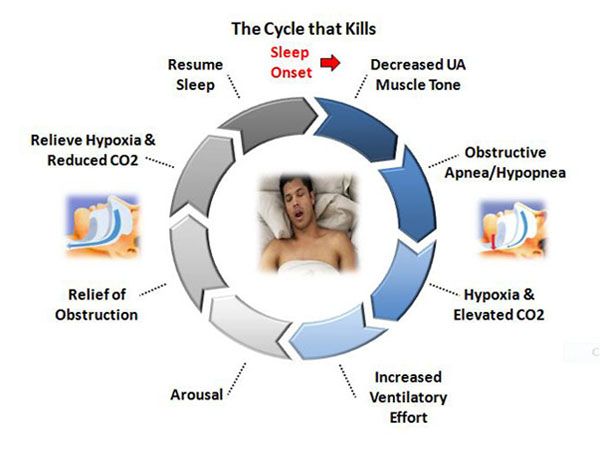
It should be noted that Ellie managed to sleep 7 hours and 48 minutes during her sleep study.  She fell asleep quickly and her arousal index was 15.1 (normal 9-16).  She spent 33.3% in REM sleep which is age-appropriate.  All of this is good, except REM sleep is where everything goes down hill.  Here is how it goes, your brain recognizes that your CO2 levels are rising, this causes an arousal.  With that arousal, you wake up a bit and trigger a bigger inhalation of air and thus increase your oxygenation and bring down the CO2 from the danger zone.  This is why people who have apnea tend to wake up alot through the night or never feel rested during the day.  Even if the quantity of sleep is there, the quality is not. 


Indexes Defined:

Apnea Hypopnea Index [AHI] looks at the number of apneas and hypopneas per hour of sleep.  For Ellie, her AHI was 4/Hr which placed her at mild OSA.  However, during REM, her AHI was >12/Hr which is severe.

SpO2 nadir is a fancy way of saying “the lowest SPO2 recorded”. Ellie’s lowest sat was at 81%.  This is not good, but it didn’t require intervention with supplemental oxygen during the sleep study.

Oxygen Desaturation Index [ODI] looks at the number of times per hour, a person’s oxygen saturations drop by 3% or more.  For Ellie, her ODI was 6.8 during stage 1&2, but then jumps to 9.5 ODI during REM sleep.  This is another reason why she has “oxygenation instability”.

Someone thought that should would take a little rest during dance class.

This blog post is turning into a term paper here so I will sign off now and write another post later on what the plan is for Ellie. 


Photobucket
 Follow us on Facebook!
http://www.facebook.com/annatheurerfitness
http://www.beachbodycoach.com/annatheurer
https://www.facebook.com/pages/The-Chronicles-of-Ellie-Bellie-Bear/216738345037166

Cecostomy Tubes R Us

Here we are - two posts in 30 days! It's scandalous, I tell you!  Seriously though, I bet you all thought that I abandoned ship and woul...